
mRNA vaccines move beyond COVID as first flu shot wins FDA approval
Moderna’s MFLUSIVA has become the first mRNA-based seasonal influenza vaccine approved in the US, bringing the technology into annual flu prevention for adults aged 50 and above after a major Phase 3 trial showed stronger protection than a standard-dose flu vaccine.
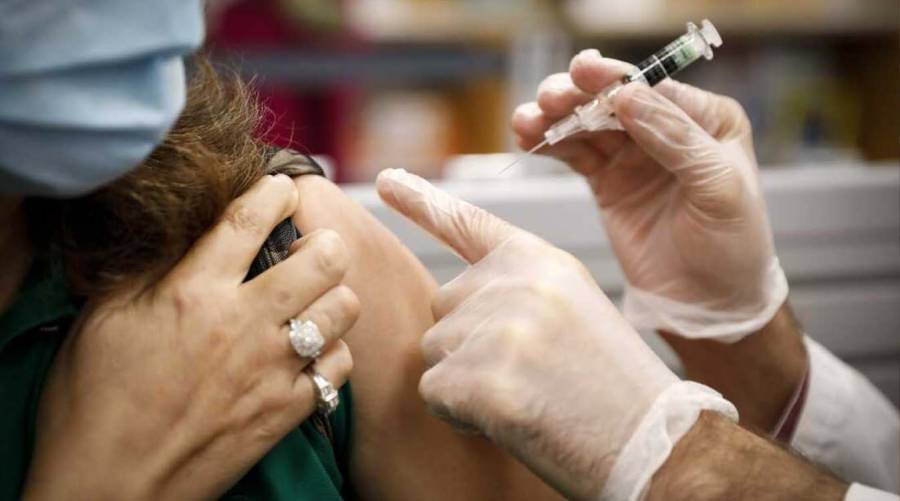
WASHINGTON: The vaccine technology that became globally familiar during the COVID-19 pandemic has reached another major milestone: the US Food and Drug Administration (FDA) has approved MFLUSIVA, Moderna’s mRNA-based vaccine against seasonal influenza, for people aged 50 years and older.
The approval makes MFLUSIVA the first mRNA seasonal influenza vaccine licensed in the United States, moving the platform into one of medicine’s most established annual vaccination programmes.
But the significance of the decision goes beyond simply adding another flu shot.
A large clinical trial found the vaccine provided 26.6% greater relative protection against laboratory-confirmed influenza illness than a licensed standard-dose influenza vaccine. Yet a closer look at the FDA decision reveals an important distinction between adults aged 50 to 64 and those aged 65 and above—one that will shape how the new vaccine is evaluated over the coming years.
More than 40,000 adults put the mRNA flu vaccine to the test
The pivotal Phase 3 trial compared Moderna’s mRNA influenza vaccine, previously known as mRNA-1010, with a licensed standard-dose flu vaccine in more than 40,000 participants aged 50 years and older.
Among 20,179 people receiving the mRNA vaccine, 411 participants, or 2.0%, developed the trial’s RT-PCR-confirmed influenza-like illness endpoint. Among 20,124 participants receiving the conventional comparator vaccine, 557, or 2.8%, developed the same endpoint.
That translated into a 26.6% relative vaccine efficacy advantage for MFLUSIVA, with a 95% confidence interval of 16.7% to 35.4%. The vaccine met the study’s predefined criteria for both non-inferiority and superiority compared with the standard-dose flu shot.
The finding was also published in the New England Journal of Medicine, where investigators reported that the mRNA vaccine was superior to standard-dose licensed influenza vaccines for preventing the trial’s confirmed influenza-like illness endpoint.
There is, however, an important point behind that 26.6% figure.
It represents relative efficacy compared with another flu vaccine, not a 26.6-percentage-point reduction in a person’s absolute risk of influenza. The actual illness rates in the primary analysis were 2.0% versus 2.8%.
That distinction is particularly important when communicating vaccine results to the public.
Why the FDA treated adults over 65 differently
Although MFLUSIVA is approved for everyone aged 50 and older, the FDA did not use exactly the same regulatory pathway for the entire population.
For adults aged 50 through 64, the vaccine received traditional approval, supported by clinical efficacy evidence.
For adults 65 years and older, the FDA granted accelerated approval, relying on immunogenicity evidence against a high-dose influenza vaccine together with supportive clinical efficacy data. FDA reviewers concluded that the available evidence was sufficient for approval while requiring additional confirmation of clinical benefit in older adults.
That requirement is not a minor technicality.
Moderna must conduct a postmarketing confirmatory study comparing MFLUSIVA with a high-dose influenza vaccine in US adults aged 65 and above. According to the FDA approval letter, the study is scheduled to begin in August 2026, with completion planned for 2029 and a final report due in 2030.
The older population matters particularly because high-dose and other enhanced influenza vaccines are already commonly used to produce stronger immune responses in seniors.
So while MFLUSIVA has cleared the FDA threshold for use in adults 65 and above, the next phase of research will examine whether its immune-response advantage translates into confirmed real-world clinical benefit against established enhanced flu vaccines.
What makes an mRNA flu vaccine different?
Traditional influenza vaccines are produced using several manufacturing approaches, including egg-based, cell-based and recombinant technologies.
MFLUSIVA instead uses messenger RNA packaged in lipid nanoparticles to provide cells with temporary genetic instructions for producing influenza antigens. The immune system then recognises those antigens and develops a response against the virus.
The approach is based on the same broad mRNA platform that became widely known through COVID-19 vaccination.
But COVID was not the only disease to move mRNA vaccines into routine medicine. Moderna’s MRESVIA, an mRNA vaccine against respiratory syncytial virus, received FDA approval in 2024. The MFLUSIVA decision now extends the platform into seasonal influenza.
That expansion is particularly significant because influenza vaccines must be reformulated repeatedly as circulating strains change.
FDA reviewers have highlighted the need for manufacturing technologies capable of rapid strain reformulation when influenza viruses undergo antigenic change. mRNA platforms may offer potential advantages because their genetic sequence can be redesigned without relying on the same biological production process used for traditional egg-grown vaccines.
That does not mean an mRNA flu vaccine will automatically outperform conventional vaccines every year. Influenza vaccine performance depends on circulating strains, vaccine matching, population immunity, age and the characteristics of each flu season.
But faster adaptability could become one of the technology’s most important advantages.
MFLUSIVA caused more short-term reactions than conventional flu shots
The FDA review also provides a detailed picture of safety and reactogenicity.
Short-term local and systemic reactions occurred more frequently with the mRNA vaccine than with comparator influenza vaccines, although FDA reviewers said they were predominantly mild to moderate and typically lasted around two days.
Among participants aged 50 to 64 who received MFLUSIVA, the most commonly reported reactions included injection-site pain in 68.7%, fatigue in 48.1%, headache in 41.9%, muscle pain in 40.6%, joint pain in 31.5% and chills in 27.5%.
Among participants aged 65 and above, injection-site pain was reported in 62.9%, fatigue in 42.1% and headache in 33.7%.
The FDA’s pooled safety analysis across four Phase 3 studies included almost 36,000 people exposed to the mRNA vaccine and a similar number receiving comparator vaccines. Reviewers concluded that the pooled analysis did not identify an overall safety concern, although continued monitoring remains part of postmarketing surveillance.
The review also examined adverse events of special interest, including neurological events and myocarditis or pericarditis. FDA reviewers reported no meaningful overall difference between the mRNA vaccine and comparator groups in these analyses.
As with any newly approved vaccine, larger-scale use can reveal uncommon adverse events that clinical trials may not be large enough to detect, making pharmacovigilance after introduction important.
Why the approval could matter beyond this particular vaccine
Influenza is unlike many vaccine-preventable diseases because the target keeps moving.
The dominant strains can change from one season to the next, forcing global health authorities and manufacturers to repeatedly update vaccine composition.
That means speed can matter.
The potential advantage of mRNA technology is not merely that it can generate an immune response. Its greater long-term significance may lie in the ability to redesign and manufacture vaccines more rapidly when circulating viruses change. Reuters noted that this flexibility is one of the reasons the technology is attracting interest for influenza prevention.
The approval therefore serves as another test of whether the mRNA platform can evolve from a technology closely associated with pandemic response into an adaptable platform for routine infectious-disease prevention.
MFLUSIVA also joins Moderna’s existing mRNA RSV vaccine, showing that commercial mRNA vaccination is now extending across multiple respiratory viruses rather than remaining confined to SARS-CoV-2.
The first season will not answer every question
There are still meaningful limits to the evidence.
FDA reviewers noted that much of the efficacy evidence came from a single influenza season, which cannot establish whether the same relative advantage will persist when substantially different strains dominate in future years.
Evidence against influenza B was also more limited than evidence involving influenza A, adding uncertainty around strain-specific performance. The FDA clinical review specifically identified residual uncertainty concerning effectiveness against B/Victoria influenza.
And for people aged 65 and older—the population that carries a particularly high burden of severe influenza—the FDA has explicitly required further clinical confirmation.
Those questions will become increasingly important as the vaccine moves from controlled trials into routine use.
Will MFLUSIVA immediately transform the flu vaccine market?
Probably not overnight.
Reuters reported that Moderna is not expected to see meaningful US revenue from MFLUSIVA until the second half of 2027, partly because the company missed the contracting cycle for the 2026 US influenza season.
That means the regulatory milestone and the commercial rollout are likely to occur on different timelines.
The scientific impact could nevertheless arrive sooner. Competing vaccine developers, regulators and public-health researchers will now have real-world evidence from an approved seasonal mRNA influenza product to evaluate.
Its performance over several seasons—not merely one successful trial—will determine whether mRNA eventually becomes a major competitor to established influenza-vaccine technologies.
What does the approval mean for Pakistan?
For readers in Pakistan, the FDA decision should be understood as a US regulatory approval, not as an announcement of immediate local availability.
Whether MFLUSIVA becomes available in Pakistan would depend on separate regulatory, commercial and supply decisions. The FDA’s approval itself applies to the United States and covers people aged 50 and above.
The broader development is nevertheless relevant to Pakistan and other countries because seasonal influenza remains a global respiratory-health challenge, particularly for older adults and people with underlying medical conditions.
More importantly, the approval signals how quickly vaccine technology is evolving.
mRNA platforms that only a few years ago were associated primarily with COVID-19 are now being developed and licensed for other respiratory diseases, potentially changing how vaccines are designed, updated and manufactured.
The bigger test begins after approval
The FDA decision answers one question: can an mRNA seasonal flu vaccine meet the regulatory standard for approval?
MFLUSIVA has now done so.
But several more consequential questions remain.
Will its efficacy advantage persist through future influenza seasons? Will faster strain updates improve vaccine matching? How will it compare with high-dose vaccines in adults over 65? Will greater short-term reactogenicity affect acceptance? And will real-world data confirm the benefits suggested by clinical trials?
The mandatory study in older adults will provide part of that answer, while future influenza seasons will provide the rest.
That is why the MFLUSIVA approval represents more than the arrival of another influenza vaccine.
mRNA technology has already moved beyond its pandemic origins. Its entry into the annual flu-vaccine market will now test whether the platform can reshape one of the longest-running vaccination programmes in modern medicine.
Stay connected with Medical News Pakistan
CLICK HERE TO JOIN the official Medical News Pakistan WhatsApp Channel for verified global medical breakthroughs, FDA approvals, healthcare innovations, clinical research updates and the latest developments shaping medicine around the world.

Advertisement
E-PAPER

Trending
Popular
Dow launches ‘Bug & Drug’ app to guide antibiotic use in Pakistan
-
Obesity linked to 229 diseases, may ...
05:28 PM, 21 Sep, 2026 -
Pakistan’s Dr. Misha Tanveer takes ...
04:03 PM, 16 Sep, 2026 -
Calorie deficit for weight loss: How to ...
06:00 PM, 24 Aug, 2026 -
Vaccine maker warns of wider TBE, ...
05:00 PM, 21 Aug, 2026
Follow us on Facebook
Follow us on Twitter
Copyright ©2026 Medical News. All Rights Reserved.

