
Cholesterol treatment is changing: Lipfendra, Inclisiran and new guidelines
New evidence on twice-yearly inclisiran, the FDA approval of oral PCSK9 inhibitor Lipfendra and broader 2026 cholesterol guidelines are reshaping how clinicians assess and treat elevated LDL cholesterol.
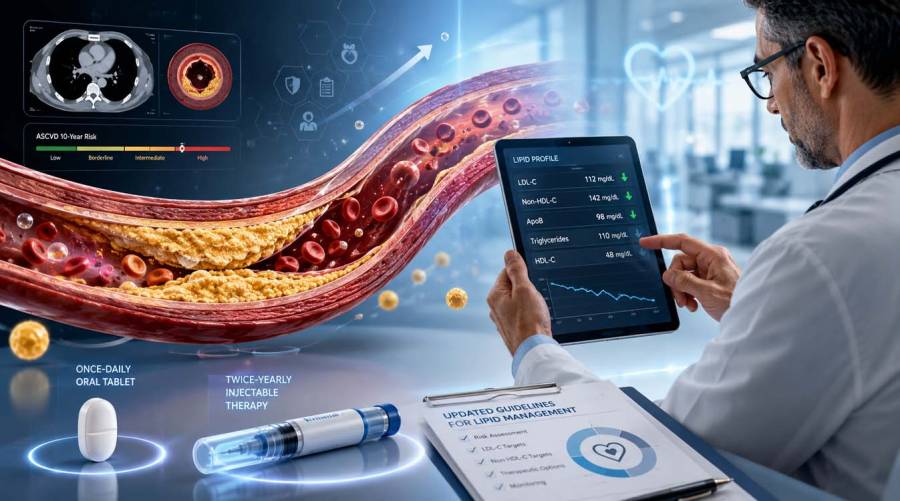
NEW YORK: Cholesterol management is entering a new phase as new lipid-lowering therapies and updated clinical guidelines are expanding the options for people who need to reduce low-density lipoprotein cholesterol (LDL-C), commonly known as “bad” cholesterol.
Three developments in particular are drawing attention: a new meta-analysis showing substantial LDL-C reductions with the twice-yearly drug inclisiran, the US Food and Drug Administration (FDA) approval of Lipfendra (enlicitide), the first oral PCSK9 inhibitor, and 2026 dyslipidemia guidelines that place greater emphasis on earlier treatment and more individualized cardiovascular risk assessment.
The changes matter because elevated LDL-C can contribute to plaque formation in the arteries and increase the risk of atherosclerotic cardiovascular disease (ASCVD), including heart attack and stroke. High cholesterol often produces no symptoms, meaning a person may not know their levels are elevated without blood testing.
Inclisiran delivers nearly 49% LDL reduction
A systematic review and meta-analysis published July 22 in JACC: Advances found that inclisiran produced a pooled mean 48.77% reduction in LDL-C compared with placebo.
The analysis included nine randomized controlled trials involving 6,355 participants and found substantial LDL-C reductions across different patient populations and background lipid-lowering treatments. The researchers noted significant variation between studies, however, meaning the pooled result should not be interpreted as an identical response for every patient.
Inclisiran is a small interfering RNA (siRNA) therapy that reduces hepatic production of PCSK9, a protein involved in regulating LDL receptors and blood LDL-C levels. Its twice-yearly dosing provides a potential advantage for patients who have difficulty maintaining adherence to more frequent medication schedules.
But an important question remains: does lowering LDL-C with inclisiran translate into fewer heart attacks and strokes?
The drug has demonstrated consistent LDL-C lowering, but cardiovascular outcomes data remain under investigation. That distinction is important when interpreting the latest evidence: a large reduction in a biomarker does not by itself establish the same magnitude of reduction in cardiovascular events.
First oral PCSK9 inhibitor changes the treatment landscape
Meanwhile, the FDA has approved Lipfendra (enlicitide) as the first oral PCSK9 inhibitor for adults with hypercholesterolemia, including adults with heterozygous familial hypercholesterolemia (HeFH). The once-daily tablet is used with diet and exercise and provides another option for patients who require additional LDL-C reduction.
The approval was supported by two randomized, double-blind, placebo-controlled trials involving 3,207 adults receiving maximally tolerated statin therapy.
In the first trial, involving adults with established ASCVD or those at high cardiovascular risk, Lipfendra produced an average 56% reduction in LDL-C at 24 weeks compared with placebo.
In the second trial, which enrolled adults with HeFH, the average reduction was 59% at 24 weeks compared with placebo.
The FDA reported that adverse-reaction frequency was similar between Lipfendra and placebo in the first trial. In the HeFH trial, diarrhea and dizziness occurred more frequently with Lipfendra, while treatment discontinuation because of adverse reactions was comparable between groups.
Importantly, these trials were designed to evaluate LDL-C lowering rather than directly establish whether Lipfendra reduces heart attacks or strokes. Its approval therefore adds a new LDL-lowering option, but clinicians will still consider the broader evidence and individual cardiovascular risk when deciding treatment.
The 2026 guidelines could bring more people into treatment
The medication advances arrive alongside a major change in how cholesterol risk is assessed.
The 2026 American Heart Association/American College of Cardiology multisociety guideline on dyslipidemia replaces the 2018 cholesterol guideline and expands the framework beyond LDL-C alone. It incorporates the AHA PREVENT-ASCVD equations for cardiovascular risk assessment, recommends measuring lipoprotein(a), or Lp(a), at least once in every adult's lifetime, supports selective apolipoprotein B testing and brings back LDL-C and non-HDL-C treatment goals, with lower targets for people at higher risk.
The guideline also expands the use of coronary artery calcium (CAC) scoring when appropriate to help reclassify cardiovascular risk.
One analysis of the new recommendations suggests their impact could be substantial.
A study published in JAMA estimated that 87.5 million US adults aged 30 to 79 — 56.6% of the target population — would be eligible for statin therapy for primary prevention under the 2026 guideline. That includes approximately 21.5 million people who would not have been eligible under the previous recommendations.
The expansion does not mean that every person should automatically start a statin. Rather, the updated framework places greater emphasis on individualized risk assessment and shared treatment decisions.
The same analysis found that the newly statin-eligible population generally had lower estimated 10-year ASCVD risk than people already eligible under earlier recommendations, illustrating how the new guideline moves toward earlier intervention in selected patients.
Why the shift toward earlier cholesterol treatment matters
The new approach reflects growing recognition that cardiovascular risk develops over years of exposure to atherogenic lipids rather than appearing suddenly when a person reaches a particular age.
The 2026 guideline therefore emphasizes identifying risk earlier, using more detailed biomarkers and risk tools, and treating patients according to their overall cardiovascular profile rather than relying on LDL-C in isolation.
Lp(a) is one example. The guideline recommends that every adult have Lp(a) measured at least once because elevated levels are often inherited and can independently increase cardiovascular risk.
At the same time, another recent study found that important treatment gaps remain. Despite the availability of effective lipid-lowering therapies, many high-risk adults are still not receiving recommended treatment.
Statins remain central despite the new therapies
The arrival of inclisiran and Lipfendra does not mean statins are being replaced.
Statins remain a foundational first-line treatment for many patients with elevated cholesterol and cardiovascular risk. Newer therapies are expanding the options for people who do not reach recommended LDL-C levels despite treatment, cannot tolerate adequate statin therapy, or have sufficiently high residual cardiovascular risk to warrant additional lipid lowering.
That creates a broader treatment landscape in which clinicians may consider statins, ezetimibe, injectable PCSK9 therapies, inclisiran and now an oral PCSK9 inhibitor, depending on the patient's risk profile and treatment needs.
The bigger change may therefore be less about one “replacement” drug and more about having more ways to achieve appropriate LDL-C reduction for different patients.
What patients and clinicians should watch next
The most important developments may now come from the evidence generated after these approvals and recommendations enter wider clinical use.
For inclisiran, cardiovascular outcomes data will help clarify whether its substantial LDL-C reductions translate into meaningful reductions in major cardiovascular events. For Lipfendra, longer-term real-world experience and outcomes research will provide additional information beyond its demonstrated LDL-C-lowering effect.
Meanwhile, the 2026 dyslipidemia guideline is likely to influence who gets screened, how cardiovascular risk is calculated and when clinicians recommend lipid-lowering treatment.
Together, these developments point toward a cholesterol-management model that is earlier, more individualized and increasingly diverse in its treatment options — while keeping lifestyle measures, appropriate screening and evidence-based clinical decision-making at the centre of cardiovascular prevention.
Important: These developments do not mean patients should start, stop or switch cholesterol medication without medical advice. Treatment decisions should be based on an individual's LDL-C levels, cardiovascular risk, medical history, tolerance, other risk factors and discussion with a qualified healthcare professional.
Stay connected with Medical News Pakistan
CLICK HERE TO JOIN the official Medical News Pakistan WhatsApp Channel for verified global medical breakthroughs, FDA approvals, healthcare innovations, clinical research updates and the latest developments shaping medicine around the world.

Advertisement
E-PAPER

Trending
Popular
Pakistan’s Dr. Misha Tanveer takes air pollution research to Europe ...
-
Calorie deficit for weight loss: How to ...
06:00 PM, 24 Aug, 2026 -
Vaccine maker warns of wider TBE, ...
05:00 PM, 21 Aug, 2026 -
FDA authorizes first robot to draw ...
06:11 PM, 20 Aug, 2026 -
One blood test for multiple cancers ...
04:52 PM, 11 Aug, 2026
Follow us on Facebook
Follow us on Twitter
Copyright ©2026 Medical News. All Rights Reserved.

